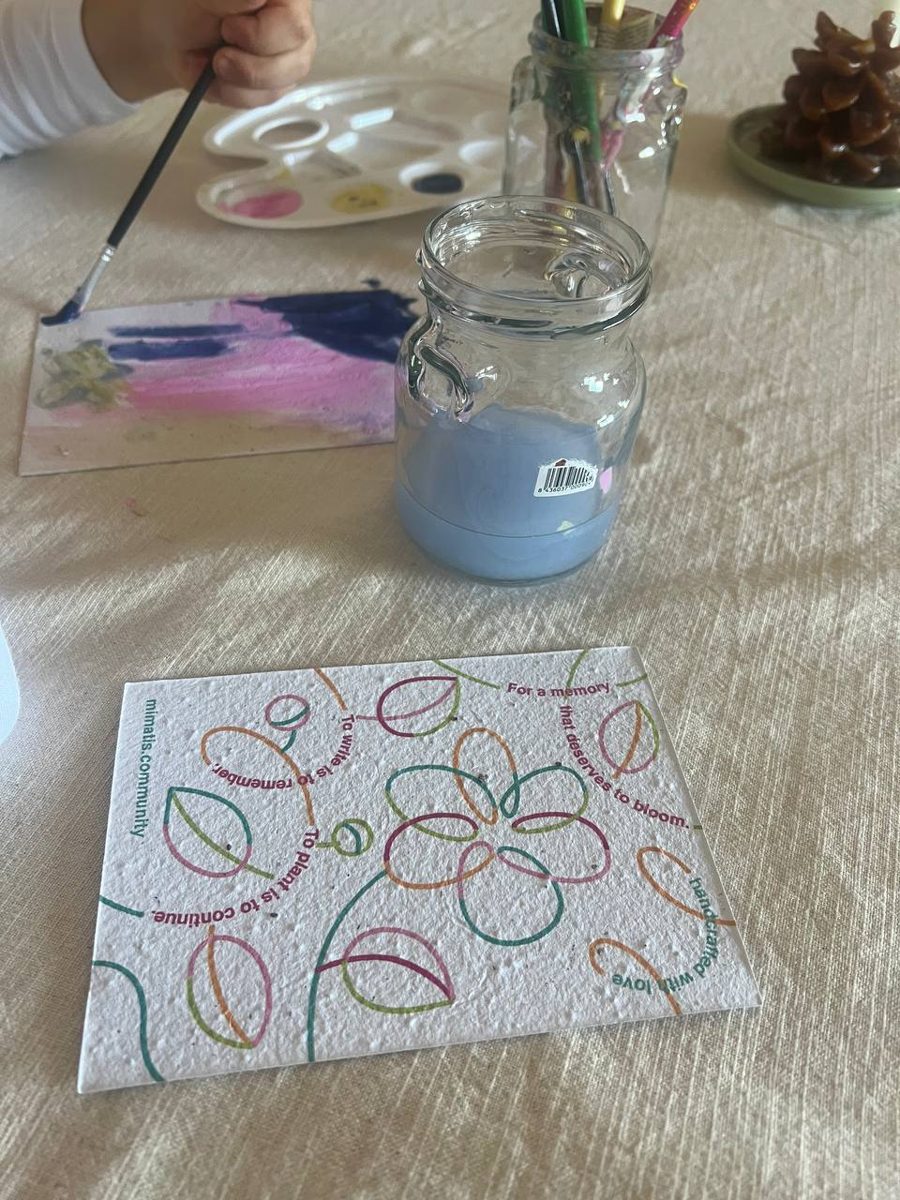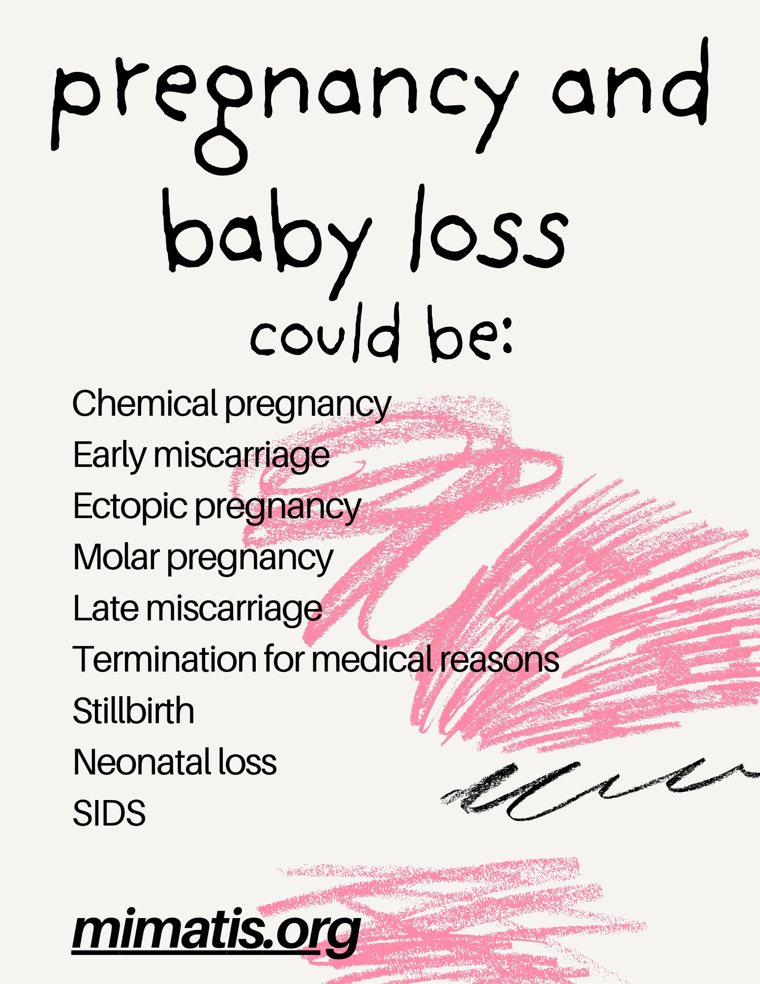




















Pregnancy and baby loss · Support around the world

For every parent
who has lost a baby.

Verified support, practical guidance and a place to remember, for parents after miscarriage, stillbirth or the death of a baby, wherever they live.

Popular:SpainUnited StatesLithuaniaUnited KingdomNetherlands

··

Plant a flower in your baby’s name in our memorial garden →Follow us on Instagram@mimatis.community

My baby’s notebook

For parents after a stillbirth. In the first days, you are told many things and remember very little. This notebook gives you the questions to ask your care team, space to write the answers, and a place to keep your baby’s name, date and the memories you want to hold on to.

Download the notebook (PDF)
How MIMATIS helps

Ways we work

For parents

Support where you are

Helplines, associations, hospital bereavement teams and funeral information, checked country by country.

With hospitals

Better care from the first hour

The hospital is where every family passes through. We are open to projects with maternity teams, shaped around what each hospital wants to achieve.

With companies

Partner with MIMATIS

Sponsor a language, bring comfort items to hospitals, or support your own teams. Companies can help us reach every parent.

Working together with
Krizinio Nėštumo Centras logo International Stillbirth Alliance logo Mamos žurnalas logo Now I Lay Me Down to Sleep logo
GlobalVerified support,
country by country
Researchthat may answer some
of your questions →
44Pregnancy losses
every minute
10+Languages in
information cards
For parents

Guidance for the first days, and the years after

Practical, honest information to read at your own pace, or to share with the people around you.

With hospitals

The hours in hospital shape the years that follow

How parents are cared for when their baby dies stays with them for a lifetime. Whether they had time with their baby, whether someone explained what was happening, whether they left with a photo, a name and a number to call: these moments shape how they grieve, often for decades.

The hospital is the one place every family passes through. That is why MIMATIS works with maternity units, midwives and bereavement teams. It is the best chance to make a difference.

Projects with hospitals

MIMATIS has several projects we would like to explore with hospitals. Every hospital is different: some already have bereavement protocols in place, others are just starting. We begin by listening to what your team wants to achieve, and shape the work around it.

We are open to

  • Creating events together, such as remembrance days and talks for staff and families
  • Support delivered in the hospital, alongside your teams
  • Digital support for parents, in their own language, before and after they go home
  • Comfort for families, such as seed letters and memory items

Tell us about your hospital and your goals

contact@mimatis.org
With companies

Partner with MIMATIS

Companies can make a real difference for families after pregnancy and baby loss: as partners, as sponsors, and as workplaces that look after their own people.

Sponsor a language

Help translate MIMATIS guidance into another language, so more parents can read it in their own.

Bring comfort to hospitals

Fund seed letters and memory items that maternity teams can give to families.

Support your own teams

Guidance and talks for managers and HR on pregnancy loss at work.

Campaigns and events

Mark 15 October with your staff or customers, or create an event together.

Write to us with an idea, or simply to start a conversation.

contact@mimatis.org

Asociación MIMATIS is a registered non-profit association in Spain, no. 633.864.

Pregnancy and baby loss could be: chemical pregnancy, early miscarriage, ectopic pregnancy, molar pregnancy, late miscarriage, termination for medical reasons, stillbirth, neonatal loss, SIDS.
Awareness

More common than most people think

Pregnancy and baby loss takes many forms, at every stage of pregnancy and after birth. Talking about it openly means more parents receive good care, and more babies are remembered.

About 15%

of recognised pregnancies end in miscarriage

1.9 million

babies are stillborn every year, one every 17 seconds

Many

stillbirths could be prevented with good care during pregnancy and birth

Up to 60%

of bereaved parents show symptoms of depression, anxiety or post-traumatic stress

Sources: UNICEF, WHO, The Lancet (2021), Trauma Care (2022).

Why MIMATIS exists

The parent who finds nothing
at 3 in the morning.

A parent who speaks the language of their country, who knows their health system, who has a supportive midwife — that parent has a chance of finding support after loss.

A parent who moved from Lithuania to the Netherlands for work, who does not speak Dutch, who does not know the term “bereavement midwife” exists, who is searching at 3am for someone who can help — that parent finds nothing.

Language, geography, and mobility are among the most overlooked determinants of bereavement care. As Europe’s population becomes increasingly mobile — with millions of parents raising families in countries that are not their own — the assumption that local, monolingual resources are sufficient is no longer valid.

MIMATIS was built to solve this. A digital-first platform with no geographic restriction — available to every bereaved parent, wherever they are, in any language, at any hour.

Support in your country

Find verified bereavement support
wherever you are

Helplines, charities, hospital bereavement teams, and funeral support — listed and verified, country by country. We keep adding more countries.

Select your country to see verified local resources

If you are in crisis right now, please reach out to your country's emergency services or a mental health line. You are not alone.

Global Resources

Find Support in Your Country

Select your country to see verified charities, helplines, hospital bereavement teams, and funeral support resources.

In memoriam

The Memorial Garden

Plant a flower in your baby’s name. It blooms here alongside flowers planted by parents around the world, and it stays here, always.

🌸  Loading flowers...

Plant a flower

Write your baby’s name, choose a flower and, if you wish, the year.

Each flower stays in the garden. We keep only the name, the flower and the year, with no email or other personal details.

A MIMATIS seed letter laid in the soil of a terracotta planter
Seed letters

A flower you can plant at home

MIMATIS seed letters are made of paper with poppy seeds inside. Write to your baby, plant the letter in a pot or a garden, and in time the words become flowers that can return every year.

A gentle activity for brothers and sisters too: they can write, or draw what they feel, and plant it together with you.

Would you like seed letters for your family or your hospital?

contact@mimatis.org

To write is to remember.
To plant is to continue.

From the MIMATIS seed letters

Research, explained

What the research says

Answers to questions parents ask after losing a baby, based on published studies. Each answer links to the original papers.

Last checked: 22 October 2026

1.9 million

babies are stillborn every year, one every 17 seconds

UNICEF, 2023 estimates
15%

of recognised pregnancies end in miscarriage, about 23 million a year

Quenby et al., The Lancet, 2021
3 in 4

stillbirths have a probable or possible cause found when full tests are done

Bukowski et al., JAMA, 2011
3 in 10

women have post-traumatic stress symptoms one month after a miscarriage or ectopic pregnancy

Farren et al., AJOG, 2020

Why did my baby die?

Often a cause can be found, but not always. In a large study where families agreed to a full set of tests, a probable or possible cause was found for about 3 in 4 stillbirths. The most common were complications of pregnancy or birth and problems with the placenta.

For about 1 in 4 babies, no cause was found even after full testing. Not finding a cause is common.

When a baby dies suddenly in the first months after birth, the main known risks relate to how and where the baby sleeps. Researchers are also looking for early signs of which babies are more vulnerable.

What the research shows
Bukowski R et al. · JAMA · 2011Causes of death among stillbirths

Full testing found a probable or possible cause for 76% of stillbirths. The most common were complications of pregnancy or birth (29%) and problems with the placenta (24%).

Fraile-Martinez O et al. · International Journal of Medical Sciences · 2024Sudden Infant Death Syndrome (SIDS): state of the art and future directions

A review of what is known about SIDS. Most deaths happen before 6 months. Known risks include sleeping on the front or side, soft bedding and overheating.

Oltman SP et al. · JAMA Pediatrics · 2024Early newborn metabolic patterning and sudden infant death syndrome

Some results of the newborn heel-prick screening were linked to a higher risk of SIDS. This is early research and is not yet used in care.

Should we agree to a post-mortem or other tests?

This is your decision. An examination of the placenta and a post-mortem are the tests most likely to explain why a baby died. In one large study, the placenta examination helped find the cause in about 2 in 3 stillbirths, and a post-mortem in about 4 in 10.

Ask the hospital what is possible where you are, for example a full or a limited examination, how much time you have to decide, and how and when you will hear the results.

What the research shows
Page JM et al. · Obstetrics & Gynecology · 2017Diagnostic tests for evaluation of stillbirth: results from the Stillbirth Collaborative Research Network

Examination of the placenta helped explain 65% of stillbirths and a post-mortem 42%. Genetic testing helped in 12%.

Will it happen again?

After a stillbirth, the risk in a next pregnancy is higher than average, but it is still low. In studies of over 3 million women, 2.5% of pregnancies after a stillbirth ended in stillbirth, compared with 0.4% for women without a previous stillbirth.

Miscarriage is common: about 15% of recognised pregnancies end in miscarriage. Repeated miscarriage is much rarer. About 2% of women have had two miscarriages and less than 1% three or more.

Ask for an appointment to go through any test results and a plan for a future pregnancy.

What the research shows
Lamont K et al. · BMJ · 2015Risk of recurrent stillbirth: systematic review and meta-analysis

Studies of over 3.4 million women: 2.5% of pregnancies after a stillbirth ended in stillbirth, compared with 0.4% without a previous stillbirth.

Quenby S et al. · The Lancet · 2021Miscarriage matters: the epidemiological, physical, psychological, and economic costs of early pregnancy loss

About 15% of recognised pregnancies end in miscarriage, around 23 million a year worldwide. About 11% of women have had one miscarriage, 2% two, and less than 1% three or more.

Is what I am feeling normal?

Strong grief, anxiety and trauma symptoms are common after losing a baby, and they can last a long time. In a large UK study, almost 3 in 10 women had post-traumatic stress symptoms one month after a miscarriage or ectopic pregnancy, and almost 2 in 10 nine months later.

Research on stillbirth describes grief, guilt, isolation and anxiety in later pregnancies, and for some parents also pride in their baby. If your feelings make daily life very hard, talk to your doctor or midwife, or a support organisation in your country.

Find support in your country →

What the research shows
Farren J et al. · American Journal of Obstetrics & Gynecology · 2020Posttraumatic stress, anxiety and depression following miscarriage and ectopic pregnancy: a multicenter, prospective, cohort study

One month after the loss, 29% of women had post-traumatic stress symptoms and 24% moderate to severe anxiety. Nine months later, 18% and 17%.

Burden C et al. · BMC Pregnancy and Childbirth · 2016From grief, guilt pain and stigma to hope and pride: a systematic review and meta-analysis of mixed-method research of the psychosocial impact of stillbirth

A review of 144 studies. Grief, anxiety in later pregnancies, grief not recognised by others, and effects on brothers and sisters were common themes. Some parents also described pride in their baby.

Gomes Beato BV et al. · Frontiers in Psychiatry · 2025Experiences and long-term repercussions of perinatal grief in women after perinatal bereavement: a meta-ethnography

18 studies of mothers a year or more after their loss. Grief was long-lasting and changed how women saw themselves. Being acknowledged by carers and others helped.

How does this affect partners and fathers?

Partners often feel they must stay strong for the mother, and their own grief is less often recognised by family, friends and carers. How men grieve varies a lot from person to person.

Fathers often keep busy, go back to work early and grieve privately. Some studies find fathers report less intense grief than mothers, but the scales used mostly capture grief that people show, so they may miss some of it. In reviews, trauma symptoms that eased over time in mothers sometimes lasted longer in fathers. Most studies are small and come from a few countries.

Read our guide for partners and fathers →

What the research shows
Obst KL et al. · BMC Pregnancy and Childbirth · 2020Men's grief following pregnancy loss and neonatal loss: a systematic review and emerging theoretical model

A review of 46 studies. Men often felt they had to support their partner, and their own grief was less often recognised by others.

Jones K et al. · Midwifery · 2019New understandings of fathers’ experiences of grief and loss following stillbirth and neonatal death: a scoping review

A scoping review. Men reported less intense and less lasting psychological effects than women, were more likely to cope by avoidance, including drinking more alcohol, and felt overlooked by health professionals.

McNeil MJ et al. · Pediatrics · 2021Grief and bereavement in fathers after the death of a child: a systematic review

A review of 21 studies of fathers after the death of a child of any age. Fathers often avoided talking about their grief and went back to work sooner. Trauma symptoms that eased over time in mothers lasted longer in fathers.

Should we see and hold our baby?

There is no right or wrong choice. A review of the research found no clear evidence that holding a stillborn baby helps or harms parents’ mental health. Mothers who held their baby were consistently glad they did.

If you are not ready, ask the hospital whether photographs, hand and footprints or other keepsakes can be made and kept for you.

What the research shows
Hennegan JM et al. · BMJ Open · 2015Contact with the baby following stillbirth and parental mental health and well-being: a systematic review

No clear evidence that holding a stillborn baby helps or harms mental health. Mothers who held their baby were consistently glad they did.

Being pregnant again

A pregnancy after loss often brings hope and fear at the same time, and it can be hard to trust that it will end well. Parents say that emotional support from their midwife or doctor made a real difference.

You can ask for extra check-ups, a named contact person, or a plan for what to do if you are worried.

What the research shows
Mills TA et al. · BJOG · 2014Parents' experiences and expectations of care in pregnancy after stillbirth or neonatal death: a metasynthesis

Parents described mixed emotions, strong anxiety and little trust that the pregnancy would end well. Emotional support from carers made the pregnancy easier.

Can stillbirth be prevented?

Some risks can be lowered. Going to sleep on your back in the last three months of pregnancy is linked to a higher risk of late stillbirth. Going to sleep on your side, left or right, is safer.

Health services advise contacting your maternity unit straight away if your baby’s movements slow down or change. A large UK trial showed that a movement-awareness campaign alone did not lower stillbirth, so good care when parents report a change matters too.

What the research shows
Cronin RS et al. · EClinicalMedicine · 2019An individual participant data meta-analysis of maternal going-to-sleep position, interactions with fetal vulnerability, and the risk of late stillbirth

Going to sleep on the back in late pregnancy was linked to about 2.6 times the risk of late stillbirth, compared with the left side. The right side carried no extra risk.

Norman JE et al. · The Lancet · 2018Awareness of fetal movements and care package to reduce fetal mortality (AFFIRM): a stepped wedge, cluster-randomised trial

A care package on baby movements in UK maternity units did not lower the stillbirth rate overall (4.40 vs 4.06 per 1,000 births), and led to more inductions and caesareans.

How common is stillbirth in Europe?

About 1.9 million babies are stillborn worldwide each year. Rates in Europe are among the lowest in the world, but they differ between countries. Between 2010 and 2021 they fell in 6 of 25 European countries, rose in 2, and did not change much in the rest.

Countries also count stillbirths in different ways, for example by weeks of pregnancy or by birth weight, so comparisons between countries need care.

What the research shows
Hug L et al. · The Lancet · 2021Global, regional, and national estimates and trends in stillbirths from 2000 to 2019: a systematic assessment

An estimated 2.0 million babies were stillborn worldwide in 2019. Progress in lowering stillbirth is too slow to meet international targets.

Kniffka MS et al. · European Journal of Public Health · 2025Stillbirth rate trends across 25 European countries between 2010 and 2021: the contribution of maternal age and multiplicity

Stillbirth rates fell in 6 of 25 European countries and rose in 2. Mothers’ age and twin or multiple pregnancies explained only a small part of the changes.

Gissler M et al. · European Journal of Public Health · 2022Clarity and consistency in stillbirth reporting in Europe: why is it so hard to get this right?

European countries count stillbirths in different ways. On average, official rates were 22% higher than research network data, so country comparisons need care.

How we choose studies

We include peer-reviewed studies that answer questions parents ask. Every study is checked by hand against the original paper, and each link goes to the paper itself. Summaries are written in plain language and are not medical advice: please talk to your doctor or midwife about your own situation.

Are you a researcher? We would like to hear about your work, check our summaries with you, or share studies that are looking for parents to take part. Write to contact@mimatis.org.

A gentle resource · For you

Guidance &
Support

Gentle, practical guidance for the days after loss — what to expect, the decisions you may face, and how to begin to remember.

When you first hear the news

Nothing prepares you for being told that your baby has died, or that your baby may die soon after birth. Until that moment, you may have been waiting and hoping to meet your baby alive, and this news can feel sudden, unreal, and impossible to take in.

It is normal to feel shocked, angry, confused, or numb. Many parents find themselves asking, “How can this be happening?” or “Why?” If the loss was unexpected, the medical team may not yet know the reason, and in many cases the cause can only be explored later.

You may also find it hard to understand what doctors are saying, or you may need them to repeat information several times. That is completely normal. The health professionals caring for you should answer your questions patiently, clearly, and with respect. Your questions do not bother them; they are part of the support you deserve.

It can also help if someone close to you reads this information and the rest of the guidance with you, so they can support you and help communicate your wishes to the medical team about your baby's birth and farewell.

Knowing and spending time with your baby

When the medical team first suggests that you see or hold your baby after childbirth, it is completely normal to feel frightened, shocked, or overwhelmed. In this moment, the idea of seeing your baby after loss can feel too painful to face.

However, most parents and couples who choose to see and hold their baby (more than 95%) later say it was a meaningful and important decision for them. Holding your baby, seeing their face, noticing who they resembled in your family, being able to love them, and saying goodbye — these are natural parts of the grieving process. Although right now it may feel like the most painful thing in the world, those moments often become some of the most precious memories you will carry.

What will my baby look like?

This is one of the most common questions parents ask. When you learn your baby has died or will die soon after birth, your first reaction may be shock, fear, or even a desire not to see your baby. This is completely normal. You dreamed of meeting a living, healthy baby — warm, rosy, and full of life.

If your baby died recently (within hours or days), they may look physically much like any other baby:

  • Their skin may be intact and beautiful
  • They may have slightly darker lips
  • Some areas of skin may be peeling slightly or have small blisters
  • They may be covered with white vernix (protective coating) and some blood
  • They may appear to be sleeping, though with less muscle tone than a living baby

If your pregnancy was earlier (between 12–20 weeks), your baby's skin may be more translucent, but they will be completely formed and beautiful.

If your baby died earlier, or there may be physical changes or malformations, you can ask the medical team to:

  • Wrap your baby in a soft blanket
  • Let you see them gently, step by step
  • Prepare them in a way that feels respectful to you

Important to know: your baby will not feel cold when you first hold them. They will still have warmth from your body. This warmth may gradually change, but you can cover your baby with blankets or keep them in the crib the hospital has prepared for you.

How much time can I spend with my baby?

The hospital should allow you to be with your baby as long as you need — this could be several hours or even longer. You have the right to:

  • Be alone with your baby — tell the staff if you want privacy
  • Ask where your baby is — when you're not with them, you can ask the staff to tell you where they are kept
  • Include other family members — grandparents, siblings, or other loved ones may also want to meet your baby. Including them can help the whole family begin to grieve and remember this new member you were expecting

The most important thing: be with the people you want to be with right now. There is no “right” way to respond to this loss.

If the hospital needs your baby for medical examination

In some cases, the hospital may need to take your baby for pathological anatomy studies (to understand why the loss occurred). You have rights in this situation:

  • You can ask questions — ask why the examination is needed, how long it will take, and what information it will provide
  • You can request to see your baby first — before any examination, you can ask to have time with your baby

Creating memories: photographs and objects

Some parents see and hold their baby while they're alive; others do so after death. But leaving the hospital with empty arms and few physical memories is incredibly difficult.

Most families who choose to create memories say it becomes precious later. Even if it feels hard now, these memories can help you grieve and remember.

If you can see or hold your baby:
  • Wash or bathe them gently
  • Dress them in clothes you had prepared, or ask hospital staff for baby clothes
  • Cover them with a soft blanket
Take photographs
  • It may feel uncomfortable now, but photos become precious memories over time
  • Photos help you remember what your baby looked like (memories fade)
  • They help introduce your baby to family, friends, and future children
  • Types of photos: baby's hands in yours, feet, you holding baby, whole family together
  • Best practice: baby in arms (not on a table), in colour (can be converted to black and white later)
Other memories to keep
  • A lock of baby's hair
  • Hospital bracelet (if baby was born alive)
  • Clothes or blanket baby was wrapped in
  • Ultrasound images
  • Any medical records or certificates
Where to go from here

More detailed guides for specific parts of this journey. Read whichever you need, whenever you feel ready.

Also available as separate pages: what to expect · letter templates · what to say · your body after loss · for partners & fathers

/ What to expect
/ Finding the right words

In moments of profound loss, words can feel impossible to find. These templates are here so you do not have to start from nothing. Take what feels right, change what does not, and make it your own.

/ What to say

When someone you love loses a baby, it can be hard to know what to say. You don’t need the perfect words — you just need to show up. This page will help you do that with care.

Please avoid saying these

Things that can cause pain, even when well-meant

These words tend to help

What to say instead

The most important thing

How to simply be present

Sometimes there are no right words. What matters most is that you showed up, remembered, and didn’t disappear. Grief can be very lonely. Your presence matters more than your words.

Say their baby’s name

Using the baby’s name — if shared — is one of the most meaningful things you can do.

Check in weeks later

A message one month or six months later means more than you know. Most people disappear after week one.

Offer something specific

“I’m bringing dinner Thursday” is far more helpful than “let me know if you need anything.”

Remember key dates

The due date, the anniversary. A simple “thinking of you today” is deeply meaningful.

/ Information cards
/ Your body after loss

You have just given birth. Your body does not know what your heart knows. This guide is for mothers after a late pregnancy loss or neonatal death — covering what to expect physically, and how to care for yourself when caring for yourself feels impossible.

If you experienced an early miscarriage, some of this may still be relevant — but please speak with your GP or midwife about what applies to your situation.

Always remember

If you are ever unsure whether something you are experiencing is normal, contact your midwife or GP. You are still a patient and you are entitled to full postnatal care, regardless of whether your baby survived.

/ For partners & fathers

Most bereavement information is written for mothers. This page is for fathers and for any partner who did not give birth: husbands, wives, boyfriends, girlfriends and co-parents. Your baby was your child too. You can be sad, angry, numb or lost, and you can need help, and none of that takes anything away from your partner’s loss.

Who we are

MIMATIS exists so that no parent searches alone for help after losing a baby.

We are a registered non-profit association, founded by parents who lost a baby. We bring together support, information and remembrance for families after pregnancy and baby loss, in every country we can reach and in the languages families speak.

A pale butterfly among soft glowing stars
Mission

To help every parent who has lost a baby find support, information and a place to remember, wherever they live and whatever language they speak.

Vision

A world where good bereavement care is not a matter of where you live or which language you speak, and where the loss of a baby is spoken about openly.

Why we exist

Support after loss exists, but it is scattered, hard to find in the first days, and usually in one language. Many parents only learn what was possible when it is too late to ask for it.

What we do

Four commitments

01

Help in every country

Parents should be able to see, in one place, the help available where they live: hospitals, associations, helplines, their rights and what to ask for. We are building country guides one by one, checked against official sources.

02

In your own language

Many families live in a country that is not their own. In the hardest days, a local language can stand between parents and the care they need. Our guides are written in English and, step by step, in the language of each country.

03

For the years that follow

Grief does not end when the first weeks pass. We explore how art, music, writing and nature help parents carry their love for their baby over years and decades, through the Journal, seed letters, music and the memorial garden.

04

Speaking about loss

Many people cannot say what a stillbirth is, or how often it happens. We raise awareness of pregnancy and baby loss, of what can be prevented, and of what good care looks like, together with hospitals, researchers and partners.

Victoria Stelmach, founder of MIMATIS
Founder

Victoria Stelmach

Victoria founded MIMATIS after the stillbirth of her daughter Maya at 34 weeks, in the Netherlands, in 2022. Living far from her home country, she saw how hard it was to find clear information and support in the first days after loss, and how much depended on language, place and chance.

As founder, she leads MIMATIS, sets its direction and builds partnerships with hospitals, associations and researchers across Europe. She brings more than ten years of experience in sales and client relationships, and the perspective of a mother of three who knows this loss from the inside.

Her aim is simple to state and hard to reach: that every parent, in any country, can find what they need after the loss of a baby, and that every baby is remembered.

contact@mimatis.org
The team

The people behind MIMATIS

Robert Stelmach

Robert Stelmach

Treasurer & Co-Founder · Europe

Robert has spent his career in technical support and enterprise client services, roles that require precision, reliability and the ability to hold complex systems together. A father of three, he experienced the loss of a daughter to stillbirth. He is committed to ensuring the organisation is run with the care and rigour the families it serves deserve.

Oksana Gorbunova

Oksana Gorbunova

Secretary & Communications · Paris, France

Based in Paris, Oksana brings extensive experience in marketing and communications. A mother herself, she believes that how an organisation communicates shapes whether bereaved parents feel seen. She is committed to helping MIMATIS reach every family that needs it, clearly and across borders.

For Maya, and every baby
who came before and after.

Asociación MIMATIS · Registered non-profit association in Spain, no. 633.864

MIMATIS Journal

Stories, research and remembrance

Parents’ stories, research explained simply, and ways to remember, written with care for families after pregnancy and baby loss.

Gintarė sitting on a striped sofa, photographed in black and white
Parents’ stories

Leo, and what I wish had been different

At 26 weeks, Gintarė learned in a Vilnius hospital that her son would not survive. She tells what happened in the weeks that followed, and what she believes hospitals could change for mothers in her situation.

19 Oct 2026 · 8 min read Read her story →
A white heart-shaped biscuit with the word BABY pressed into it, on a speckled plate among large green monstera leaves
Fathers & partners

Fathers, too: the grief that is easy to miss

After a baby dies, people ask how the mother is. Research suggests fathers and partners grieve too, often quietly, and are asked far less. What studies show, and what seems to help.

23 Oct 2026 · 5 min read Read the article →
A space to pause: gentle music by MIMATIS
Music

A space to pause

If today feels overwhelming, let this gentle music be a little space to pause, breathe, and simply be. Created by MIMATIS for parents navigating loss, grief and anxiety.

Music · YouTube Listen on YouTube ↗
Not every loss is the same
Awareness

Not every loss is the same. Do we know what we mean?

“Pregnancy loss” covers many different experiences, and most people could not say what a stillbirth is. An essay on the words we use, what surveys show, and why speaking more clearly matters.

17 Oct 2026 · 6 min read Read the article →
A green envelope holding a MIMATIS seed letter, resting on leaves
Art & Memory

Seed letters: words that grow into flowers

Write to your baby on paper filled with poppy seeds, plant it, and watch the words become flowers. A ritual for the first weeks, for the years that follow, and for brothers and sisters.

16 Oct 2026 · 4 min read Read the article →
15 October, Pregnancy and Infant Loss Remembrance Day poster
Across Borders, Across Grief

15 October: how Europe remembers

From a conference on perinatal grief at Hospital de Sant Pau in Barcelona to the Wave of Light at 7 pm: how the remembrance day was marked across Europe in 2026.

16 Oct 2026 · 4 min read Read the article →
Sounds of Stillness — a short film about stillbirth and grief
Short Film

Sounds of Stillness

An experimental short documentary about stillbirth and silent grief — released on Mother’s Day, and filmed on Mother’s Day two years earlier.

Short film · YouTube Watch the film ↗
Victoria with her baby — Mamos žurnalas feature
In the Press

“I lived through my child’s birth, knowing they had already died”

Victoria’s own story, featured in the Lithuanian magazine Mamos žurnalas — losing her daughter Maya, and the path that led her to build MIMATIS.

Mamos žurnalas · In Lithuanian Read the feature ↗
A small heart, from Gintarė’s story about her son Leo
In the Press

“My little Leo, and what I wish had been different”

Gintarė’s story about her son Leo, published in the Lithuanian magazine Mamos žurnalas. You can also read it in English here in our Journal.

Mamos žurnalas · In Lithuanian Read the feature ↗
A heart-shaped biscuit iced with the word Baby
History & Literature

“No one ever told me grief felt so like fear.”

After losing his wife Joy, C.S. Lewis wrote one of the most honest accounts of grief ever published. What he described mirrors what bereaved parents feel today.

3 min read Read the article →
A small porcelain angel beside candlelight
Stories of Meaning

Charles Darwin lost his daughter Annie at ten years old

What his private letters reveal about grief, love, and the limits of reason — and how loss shaped one of history’s greatest minds.

3 min read Read the article →
Dummies and handwritten notes tied to a memorial tree
Healing Through Art

Memory boxes — what to put in them, and why they help

A memory box is not about preserving grief. It is about acknowledging that your baby existed and that their existence mattered.

3 min read Read the article →
Nature & Grief

Why grieving people seek water

Rivers, oceans, lakes. Research on the nervous system is beginning to explain why so many bereaved parents are drawn to water after loss.

4 min read Read the article →
New Research

When grief lives in the body — what the science says

Up to 60% of bereaved parents show symptoms of depression, anxiety or post-traumatic stress. Research helps explain why grief is felt in the body.

2 min read Read the article →
Share your story

When sending an email, I agree to my story being published on mimatis.org and republishing my story and/or image on MIMATIS social media channels. We very much appreciate your submission. Please note that we will use our discretion when publishing stories and images on our website.

Parents’ stories

Leo, and what I wish had been different

At 26 weeks, Gintarė went to hospital in Vilnius with back pain. She learned there that her son would not survive. She shares what happened in the weeks that followed, and what she believes hospitals could change.

Gintarė, photographed in black and white, sitting on a striped sofa and looking over her shoulder
Gintarė shared her story with MIMATIS and gave permission for it to be published. It has been lightly edited for clarity. It describes a stillbirth and difficult experiences in hospital.

In 2021 I became pregnant, and my baby was due in December. It was my first pregnancy, and everything was going well, just as in all the pregnancy books and stories.

Week 26

At 26 weeks I felt pain in my back. I did not even think that something could be wrong with my baby.

I went to the emergency department of a hospital in Vilnius. The resident said they would check the baby first and then send me to other doctors about my back. As soon as she started the ultrasound, I saw her face drop. She called a doctor straight away, who said that my baby’s organs were full of fluid and a professor needed to do an ultrasound immediately. From what she could see, she said, the baby should already have died, or would die in my womb within a few days.

This was in late August 2021, during COVID, and my husband was abroad. I was on my own. The doctor asked if I wanted to go home and collect my things, as I would be admitted to hospital. Luckily my belongings were in my car, so I did not have to drive in that state.

When I came back, the professor and other doctors repeated the ultrasound and confirmed that my baby boy had fetal hydrops, but they could not find the cause. Many tests followed. I was sent to a geneticist, who suspected a heart defect but could not confirm it. Later, paediatric cardiologists confirmed that one of my baby’s heart valves was positioned too low, and that this condition is not compatible with life.

Alone in hospital

Two days later my husband arrived from abroad. I begged the doctors to let him in, because I needed his support so much. Under the COVID rules he had to isolate for two weeks after travelling, and I understand that. But the doctor’s words destroyed me. She asked: “What do you need your husband here for?”

My mum was allowed to visit for a few hours each day. Time dragged. At the weekend no doctors were working, and I was waiting for the results from the cardiologist and the geneticist, still believing something might change. I asked the nurses whether it could, but they did not know anything. They only knew that they had to give me medicines to help my baby’s lungs mature.

My mum asked one of the nurses what would happen to the baby after the birth. It was a nurse I had not seen before. She answered my mum, and I heard it too: “The baby will be thrown away with the biological waste.” She said it with an ironic smile. I was in no condition to interrupt her and tell her how many weeks pregnant I was.

As soon as I was admitted, a psychologist was sent to my room. I still could not believe what was happening. We spoke a few sentences, and I did not like her suggestions, such as eating ice cream in different flavours and telling my baby which flavour it was. I asked her to leave. After that there was no social worker, nothing. I only heard a doctor shouting at the nurses: “Give that woman some sedatives.”

Twelve doctors in one room

Then there was a medical team meeting. Twelve doctors sat around the room, and I sat on a chair in the middle. Each specialist told me that my baby would certainly die, but that they did not know when: maybe in a few days, maybe at 40 weeks, maybe during labour. I remember how frightening it was. I still did not believe this was happening to me. The doctors spoke from a professional perspective, as if it were an everyday case, while also letting me know that this does not happen often.

I did not ask many questions. All I wanted was to cry. Before the meeting I had read online that in some countries surgeons operate on a baby’s heart before birth, but I was told my baby was too small for this. I also asked whether I could have a caesarean section instead of a vaginal birth, and the doctors explained why not.

Four weeks of waiting

After that they let me go home and asked me to come back every week for a check-up. For three weeks I went back. In the fourth week I was told that my baby’s heart was no longer beating. That same morning I was admitted to hospital to give birth.

The birth

I asked for an epidural. At first the doctors said morphine would be enough: as the baby had already died, it would do less harm than an epidural. I insisted, because it was too hard to bear the emotional pain and the physical pain at the same time. By the time the anaesthetist came, it was too late. She tried four times, and the epidural did not work.

I do not know whether she had been told that I was having a stillbirth, but while preparing the epidural she was showing her colleague photos of her newborn grandchild, while I was in pain, losing my child. I had been in pain from 10 in the morning until 10 at night and had no strength left. They asked me to put on a hair net myself. I could not lift my arms, and they said they would not do the epidural until I put it on. They had asked my husband to leave, so he could not help me.

A nurse, a midwife and a doctor were with me during the birth. The midwife was very kind and supported me emotionally, like a mother. I think her name was Jūratė. After so much stress I forgot to ask for her details, and I really wanted to thank her later. I will always be grateful to her.

A small red outline heart tattooed on a wrist, beside a red string bracelet with a gold angel charm

Our decision not to see him

My husband and I had decided that we did not want to see our baby after the birth. We wanted to keep him in our hearts, not in a graveyard. Jūratė told us that this had happened to her own mother, who deeply regrets not seeing her baby. During the birth I kept my eyes closed. The doctor asked if I wanted to hold him, and Jūratė told her that we had decided not to. The doctor said: “How can you not see your own child?”

I had four weeks to think about it, and at the time I believed not seeing him would be better for me. Now I regret refusing to see my baby, Leo. I hope my story can lead to changes in hospitals that help mothers in this situation to be better prepared.

What I would change in hospitals

  • One doctor responsible for each mother. A meeting with twelve specialists telling you it is all over is a lot to take in, and a woman in my condition may not be able to think clearly, ask questions or understand what is happening. During my week in hospital the doctors kept changing, and the doctor at each weekly check-up was different. I no longer knew who was responsible for what, or who knew my situation. One named doctor, to whom the mother can bring all her questions, would help.
  • More care around pain relief. Please be more sensitive about the epidural and do not delay it. Going through labour without one, and without a crying baby at the end, is too much pain.
  • Nurses must know the situation, not only the doctors.
  • A psychologist who stays involved. The psychologist should attend the medical team meeting and other appointments, so they can see how the mother is really doing. One conversation may not be enough to understand her. In my first hours in hospital I did not believe what was happening and did not want to speak to anyone, and from the few sentences we exchanged, I do not think the psychologist could see how I was really feeling.
  • Information before and after the birth. A psychologist or a social worker should speak with the mother before and after labour, explain all the options for burying the baby, and explain how important it can be to see the baby and to say hello and goodbye.
  • A quieter room. I gave birth in a room at the very end of the corridor, and the staff let me stay there afterwards so that I would not be moved to a room with women whose babies were alive. But the room was still on the same corridor as the other labour rooms. It was very hard to hear women scream in pain and then grow calm when they heard their babies cry. I spent more than 24 hours in that room. A more separate room would make a great difference.

Gintarė

Support for parents after loss is listed in our country guides, including Lithuania. If you would like to share your own story with MIMATIS, write to contact@mimatis.org.


Awareness

Not every loss is the same. Do we know what we mean?

“Pregnancy loss” has become the phrase for many different experiences. Surveys suggest most people could not say what a stillbirth is, or how often it happens. An essay on the words we use, and why they matter.

MIMATIS graphic: Not every loss is the same. Miscarriage, stillbirth, neonatal loss and infertility, each explained in one sentence.

Ask a group of mothers, even mothers of several children, to explain what a stillbirth is. Many will hesitate. Some will say it is a very late miscarriage. Others will think it is something that happened in the past, or somewhere else. Very few will know that it happens to around 1.9 million babies a year worldwide, or that in some European countries several babies are stillborn every day.

This is not a failure of the people asked. It reflects how rarely these losses are named. Over the last decade, “pregnancy loss” has become the gentle, inclusive phrase used by charities, hospitals and the media, MIMATIS included. It has done real good. But it is worth asking whether one phrase can carry so many different experiences, and what is lost when it tries to.

What the words actually mean

“Pregnancy loss” can describe any of the following. They differ in how far the pregnancy had come, what happens to the mother’s body, what parents are entitled to, and how others respond.

  • Biochemical pregnancy (often called a chemical pregnancy): a pregnancy detected by a pregnancy test that ends before it can be seen on an ultrasound scan.
  • Early miscarriage: the loss of a pregnancy in the first trimester, the most common form of loss.
  • Ectopic pregnancy: a pregnancy that develops outside the womb, most often in a fallopian tube. It cannot continue and can be dangerous for the mother.
  • Molar pregnancy: a rare condition in which the placenta does not develop normally, so the pregnancy cannot continue.
  • Late miscarriage: a loss in the second trimester, before the point at which a country counts a stillbirth. Many mothers give birth to their baby.
  • Termination for medical reasons: ending a wanted pregnancy after a serious diagnosis for the baby or a risk to the mother.
  • Stillbirth: a baby who dies after that point, before or during birth. The mother goes through labour and birth, and her body responds as after any birth.
  • Neonatal death: a baby who is born alive and dies in the first weeks of life.
  • Sudden infant death: the sudden, unexplained death of a baby in the first year, often during sleep.

And then there is a loss that has no body to hold and no date to remember: infertility, the grief for a child who was hoped for and imagined, but never arrived.

Pregnancy and baby loss could be: chemical pregnancy, early miscarriage, ectopic pregnancy, molar pregnancy, late miscarriage, termination for medical reasons, stillbirth, neonatal loss, SIDS.

The same baby, different words

Even the line between a miscarriage and a stillbirth is not fixed. It is drawn by law and by medical guidelines, and it moves from one country to the next. In the United States, Canada and Australia a baby who dies from 20 weeks is counted as stillborn. In the United Kingdom and Ireland the line is 24 weeks. Most countries in the European Union use 22 weeks, a few use 28, and Norway uses 12. For comparing countries, the World Health Organization uses 28 weeks.

In practice, this means a baby who died at 23 weeks could be counted as stillborn in France and as a late miscarriage in the United Kingdom. For the parents, the baby, the labour and the grief are the same. What changes is whether the birth is registered, whether a funeral is required, and what leave a mother is entitled to. Our country guides for Spain, France and Austria show how differently these lines are drawn, even between neighbours.

A baby who died at 23 weeks could be stillborn in France and a late miscarriage in the United Kingdom.

What people actually know

Research suggests the gap in understanding is wide:

  • In a national survey of 999 adults in Ireland, only 17% knew how common stillbirth is, and 56% could not name a single risk factor.
  • In an Australian survey of 344 people, most of them women, only 25% knew that around six babies are stillborn in Australia every day. A third believed that babies move less late in pregnancy because they run out of room, a myth that can delay care.
  • In a survey of over 1,000 adults in the United States, 55% believed miscarriage is uncommon, happening in fewer than 6% of pregnancies. A 2021 Lancet review puts it at around 15% of recognised pregnancies, about 23 million a year worldwide.
  • In the United Kingdom, a 2023 survey found that half of all adults had been affected by pregnancy or baby loss, themselves or through someone close to them.

So these losses are common, and they touch most families, yet many people do not know what they are, how often they happen, or what can be done.

Does “pregnancy loss” help or hide?

The umbrella term has helped in important ways. It replaced harsh clinical language: a European consensus of specialists in 2015 recommended “pregnancy loss” and “miscarriage” instead of “spontaneous abortion”, noting that patients prefer these words. It gives everyone a shared place to stand, so that a woman after an early miscarriage and a family after a stillbirth can both feel included in a remembrance day or a support group. And it is easier to say out loud.

But a single phrase can also blur what is different. After a stillbirth, a mother has given birth. Her milk may come in. There may be a funeral, a name on a register, a birth certificate or none at all. “We lost the pregnancy” can sound, to a parent who held their baby, as if the baby is missing from the sentence. The writer Rebecca Little described in STAT how, after her own losses, no available term seemed to fit, and how that left her and many others without words for what had happened.

Vague language also has practical costs. If people do not know that stillbirth exists, they do not know to ask about it. If they believe babies naturally move less before birth, they may wait when they should call. If friends and employers think every loss is “early”, they may expect a mother back at work in days, when she has just given birth.

So, should we speak about it more?

Yes, and more precisely. Not to rank losses, because grief is not measured in weeks, but so that each one can be recognised for what it was. That can start with small things:

  • Use the words parents use. If a mother says her son was stillborn, say stillborn. If she says her baby, say baby. If she uses a name, use the name.
  • Know the signs. Maternity services advise pregnant women to contact their maternity unit straight away if their baby’s movements slow down, stop or change, and not to wait until the next day.
  • Learn what the words mean. Knowing the difference between a miscarriage, a stillbirth and a neonatal death helps families, friends and colleagues respond with the right care.
  • Talk about it outside of loss. In antenatal classes, in schools, at work. Information is easier to hear before it is needed.

“Pregnancy loss” opened the door to talking. The next step is to say clearly what happened, and to name the babies it happened to.

Sources

Nuzum et al., The public awareness of stillbirth: an Irish population study, BJOG 2018 · Pollock et al., Knowing your audience: stillbirth knowledge in Australia, Women and Birth 2022 · Bardos et al., A national survey on public perceptions of miscarriage, Obstetrics & Gynecology 2015 · Quenby et al., Miscarriage matters, The Lancet 2021 · Tommy’s and partner charities, Baby Loss Awareness Week survey 2023 · Pregnancy Loss Research Group, UCC, The definition of stillbirth: a rationale for change, 2021 · Kolte et al., Terminology for pregnancy loss prior to viability (ESHRE), Human Reproduction 2015 · Rebecca Little, The inadequate language of pregnancy loss, STAT 2024 · UNICEF Data, stillbirth estimates 2023

Fathers & partners

Fathers, too: the grief that is easy to miss

After a baby dies, people ask how the mother is. Research suggests that fathers and partners grieve too, often quietly, and are asked far less. What studies show, and what seems to help.

A white heart-shaped biscuit with the word BABY pressed into it, on a speckled plate among large green monstera leaves

After a baby dies, the first question people ask is how the mother is. It is the right question. Her body has gone through birth or miscarriage, and the loss is physical as well as emotional. But the question is often not followed by a second one, about the father or partner, who also lost a child.

A grief that is easy to miss

Researchers who reviewed 46 studies of men’s grief after pregnancy loss and neonatal death describe it as “double disenfranchised”: the loss is often not recognised as the death of a baby, and it is often not recognised as a grief that a father is allowed to have. Men described pressure to be the supporter and to look strong. They also described care that centred on the mother, and limited paid leave from work. All of this, the authors say, made grief harder.

A review by Tommy’s National Centre for Miscarriage Research, covering earlier studies of 231 men, found something similar after miscarriage. Many men felt they were “expected to be unaffected emotionally by pregnancy loss”. As a result, they often did not ask for support, or were not offered it. Many felt like observers in their partner’s care.

Many men felt they were “expected to be unaffected emotionally by pregnancy loss.”

What it can look like

A father’s grief does not always look the way people expect. In the reviews, many men kept busy, went back to work quickly or took on practical tasks, and many grieved in private. A scoping review of studies on fathers after stillbirth and neonatal death found that men were more likely to cope by avoidance, including drinking more alcohol, and that they felt overlooked by health professionals. A review of 21 studies of fathers after the death of a child, of any age, found that fathers often avoided talking about their grief and returned to work sooner. In some of those studies, trauma symptoms that eased over time in mothers lasted longer in fathers.

There is a caution in the research. Several studies find that fathers report grief that is less intense or shorter than mothers’. But the scales used mostly capture grief that people show, and the researchers warn that they may miss what fathers keep to themselves. Most studies are small and come from a few countries. They cannot say how any one father will grieve.

The birth, and what a father sees

Fathers are often present. In a 2026 interview study of ten fathers in the United States and Canada after a stillbirth, fathers who supported their partners through a difficult labour described distress that fits secondary traumatic stress. They also described bonding with the baby during pregnancy, valuing time with the baby after the birth, and finding that photographs, keepsakes and rituals helped them remember. Some found peer support groups helpful. Others disliked group formats, and few had a therapist who understood pregnancy loss. The authors note that all ten fathers were white and non-Hispanic, so the findings may not apply to everyone.

What seems to help

The studies do not offer a cure, but they point in the same direction:

  • Being asked. A direct question about how he is, from family, friends and the hospital team, not only about how she is.
  • Being included in care. Clear, jargon-free explanations and follow-up contact for fathers as well as mothers.
  • Support in a form that suits him. The authors of the large review suggest activity-based options, contact with other fathers, online resources, male support workers and counselling for couples. In the UK, Sands runs men-only online meetings and football teams for bereaved fathers.
  • Time with the baby, and something to remember. Fathers in the 2026 study valued time with their baby, photographs and keepsakes.
  • Time away from work. Researchers call for clearer, reviewed bereavement leave policies.

If you are a father reading this

Your baby was your child too. You do not need to compare your grief with hers, or prove that it is big enough. Our guide You are grieving too covers what to ask for in hospital, the practical tasks that often fall to fathers, work, and where to find support made for men. The helplines for your country are on Find Help, and you can plant a flower with your baby’s name in the memorial garden.

If you love a father

Ask him how he is, not only how she is. Use the baby’s name if he has shared it. Do not wait for him to bring it up: studies suggest many men feel expected to say nothing. Our guide What to say, and what not to say has words that help.

Recognising a father’s grief takes nothing away from a mother’s. It gives the two of them a better chance of understanding each other, and it gives him a place to say that he lost a child too.

Sources

Obst et al., Men’s grief following pregnancy loss and neonatal loss: a systematic review and emerging theoretical model, BMC Pregnancy and Childbirth 2020 · Jones et al., New understandings of fathers’ experiences of grief and loss following stillbirth and neonatal death: a scoping review, Midwifery 2019 · McNeil et al., Grief and bereavement in fathers after the death of a child: a systematic review, Pediatrics 2021 · McDonough et al., Father’s experience of fetal death: a secondary analysis, Death Studies 2026 · Tommy’s National Centre for Miscarriage Research, Improving miscarriage support for men · Sands, Pregnancy and baby loss support for men

Art & Memory

Seed letters: words that grow into flowers

MIMATIS seed letters are made of paper with poppy seeds inside. You write to your baby, plant the letter, and in time the words become flowers. A small ritual for the first weeks, and for the years that follow.

A sage-green envelope with a MIMATIS seed letter inside, resting on green leaves among daisies

Some things are hard to say out loud. A letter gives them a place. A seed letter goes one step further: once it is written, it can be planted, and what you wrote becomes part of something that grows.

Each MIMATIS seed letter is handcrafted from paper with poppy seeds set into it. The card carries a simple line drawing of flowers and leaves in turquoise, pink, orange and green, and three short lines: to write is to remember, to plant is to continue, and for a memory that deserves to bloom. It comes in a soft green envelope.

Why poppies

Poppies have been a flower of remembrance for more than a century. They are also generous plants. They grow easily, they flower in late spring and early summer, and they drop their own seed. Where poppies have flowered once, they often return the next year, and the year after, without being planted again.

That is what makes them right for a letter to a baby who died. You plant the letter once. The flowers can come back every year.

How to plant a seed letter

  • Write first. Use a pen or pencil. Write as much or as little as you want: your baby’s name, a date, a few words, a whole letter.
  • Choose a place. A garden bed, a balcony pot or a window box, somewhere with plenty of light.
  • Plant it close to the surface. Lay the letter flat on the soil and cover it with only a thin layer, a few millimetres. Poppy seeds need light to start growing.
  • Keep it damp. Water gently so the paper stays moist while it softens and the seeds wake. The paper breaks down into the soil.
  • Wait. Poppies sown in autumn often flower the following late spring. Sown in spring, they can flower that summer.
A seed letter laid in the soil of a terracotta planter, partly covered with earth

A letter for the years that come later

Grief after the loss of a baby does not end on a set date. It changes shape. The due date, the first birthday that never happened, the year your baby would have started school: these days arrive whether or not anyone else remembers them. Many parents describe their baby as still part of their lives ten, twenty and thirty years later.

A seed letter does not have to be written in the first weeks. It can be written on an anniversary, on 15 October, on a birthday, or on an ordinary day when you want to say something. Some families write one every year. Each time, the flowers that follow are new, and so is what you wrote.

And when poppies return on their own in early summer, there is something to look at and to name. A place in the garden that belongs to your baby.

You plant the letter once. The flowers can come back every year.

A gentle activity for brothers and sisters

Children grieve too, often in short bursts and in ways adults do not expect. They may not have the words, and they do not always want to talk. A seed letter gives them something to do with their hands.

A child painting with watercolours at a table, with a MIMATIS seed letter in the foreground
  • Children who can write can write to their brother or sister: what they would have shown them, what they feel today, or simply a name.
  • Younger children can draw or paint. Colours, shapes, a picture of the family. There is no right way to do it.
  • Plant it together. Let the child choose the place, cover the letter with soil and do the watering.
  • Watch it grow. Checking for the first shoots gives a child a reason to return to the place and to talk about the baby, in their own time.

For many children, seeing flowers come up where they planted their letter is a way of understanding that love continues, even when someone has died. It is also something the whole family can share, each with their own letter.

Write, plant, remember

A seed letter is small. It asks for nothing more than a few words, a little soil and some patience. What it gives back is a place to return to, and flowers that bring life to a day that may otherwise be hard.

If you would like to know more about MIMATIS seed letters, or would like some for your family or your hospital, write to us at contact@mimatis.org.

Related

Memory boxes: what to put in them, and why they help · Plant a flower in the MIMATIS memorial garden · Guidance for brothers and sisters

Across Borders, Across Grief

15 October: how Europe remembers

Pregnancy and Infant Loss Remembrance Day is marked in hospitals, churches, town halls and homes across Europe. Here is how it was observed in 2026, from a hospital in Barcelona to candles lit at seven in the evening in every time zone.

MIMATIS poster: 15 October, Pregnancy and Infant Loss Remembrance Day, with a paper-collage butterfly and flowers

Every year on 15 October, families remember babies who died during pregnancy, at birth or soon after. The day covers miscarriage, stillbirth, ectopic pregnancy, termination for medical reasons, sudden infant death and the death of a newborn. It began in the United States in the early 2000s and is now observed in many countries, often under a local name.

The best-known tradition is the Wave of Light. At 7 pm local time, people light a candle and leave it burning for at least an hour. As 7 pm moves from one time zone to the next, the candles form a continuous line of light around the world.

Barcelona: a day of reflection at Hospital de Sant Pau

On Thursday 15 October 2026, Hospital de la Santa Creu i Sant Pau in Barcelona held its second conference on perinatal grief, the II Jornada sobre el Dol Perinatal, in the hospital’s assembly hall from 3 to 5 pm. Its theme was the family facing perinatal loss, and how to understand, accompany and remember.

The programme brought clinical practice and family experience into the same room:

  • A talk on the cold cot (bressol fred): a cooled crib that lets a baby stay with the family for longer, so parents can spend time together, make memories and say goodbye at their own pace.
  • A panel of family testimonies, in which parents spoke about their lives after the death of a baby, the importance of feeling accompanied, and why this loss should be visible.
  • An open discussion between speakers, families and the audience.
Programme cover: II Jornada sobre el Dol Perinatal, 15 October, Hospital de Sant Pau, Barcelona

Across Spain, the day is known as the Día Internacional del Duelo Gestacional, Perinatal y Neonatal. Many town halls read a manifesto prepared by FEDUP, the Spanish federation of perinatal grief associations. The 2025 manifesto called for three things: legal recognition of every baby who dies, whatever the stage of pregnancy, with the option of registering a name; grief-care protocols in every public and private hospital; and specialised training for health, administrative and funeral staff.

United Kingdom and Ireland: Baby Loss Awareness Week

In the UK and Ireland, 15 October closes Baby Loss Awareness Week, which ran from 9 to 15 October in 2026. Churches, hospitals and universities held services of remembrance during the week, many ending with the Wave of Light on the Thursday evening.

In Ireland the week reached its 24th year. In Cork, the Pregnancy Loss Research Group at University College Cork organised a study day for maternity staff, a multi-denominational service of remembrance and an exhibition on termination of pregnancy for fetal anomaly. Cork University Maternity Hospital was lit in blue and pink on the evening of 15 October. The national health service (HSE) also launched a new e-learning programme for maternity staff on supporting people after pregnancy and infant loss.

France: journée mondiale de sensibilisation au deuil périnatal

In France, maternity units and associations mark the day with gatherings for families and staff. Last year, for example, the Centre Hospitalier Sud Essonne held a morning workshop for its teams on caring for families after perinatal loss, followed by an afternoon of remembrance with speeches, songs, the planting of flower bulbs and a support group for parents. Associations such as AGAPA, SPAMA and Nos Tout-Petits organise ceremonies and groups in many regions.

Italy: BabyLoss Awareness Day

In Italy, the association CiaoLapo has organised the day since 2007, with free events in dozens of cities and an Onda di Luce, a wave of light, at 7 pm. In recent years, monuments such as the Porta Praetoria in Aosta have been lit in pink and blue.

Germany and Austria: Sternenkinder

In German-speaking countries, babies who die before or around birth are often called Sternenkinder, star children. Hospital chaplaincies and parishes hold services around 15 October. In Regensburg, for example, a service for parents and families took place on 15 October 2026 at 5 pm in the hospital church of St. Hedwig. Many families in Germany and Austria also take part in the Worldwide Candle Lighting on the second Sunday of December.

Taking part, wherever you are

You can mark the day in a simple way: light a candle at 7 pm, write your baby’s name, visit a place that matters to you, or join a local service. If you would like your baby’s name to be part of a shared place of remembrance, you can plant a flower in the MIMATIS memorial garden. For support and practical information in your country, see Find Help, including our full guides for Spain, France and Austria.

Sources

Hospital de la Santa Creu i Sant Pau, programme of the II Jornada sobre el Dol Perinatal (15 October 2026) · FEDUP manifesto 2025 · UCC Pregnancy Loss Research Group, Baby Loss Awareness Week 2026 · Tommy’s, Baby Loss Awareness Week 2026 · Wave of Light service, Felixstowe · FHF, Centre Hospitalier Sud Essonne · Quotidiano Sanità, CiaoLapo · Gazzetta Matin, Aosta · Bistum Regensburg, Sternenkinder service

History & Literature

“No one ever told me grief felt
so like fear.”

After losing his wife, C.S. Lewis wrote one of the most honest accounts of grief ever published. What he described mirrors what bereaved parents feel today.

“ ” A GRIEF OBSERVED  ·  C.S. LEWIS  ·  1961

In 1960, the writer C.S. Lewis lost his wife Joy Davidman to cancer. They had been married for only four years — a late and unexpected love that transformed both of them. What followed her death was not what Lewis anticipated.

He had written extensively about suffering from a philosophical distance. He had theorised about grief, explained it, made it comprehensible in the abstract. Then Joy died, and he found that none of it applied.

Grief felt like fear

In the raw private journals he kept in the weeks after her death — later published as A Grief Observed — Lewis described an experience that contradicted everything he had expected. The most striking observation, and the one that has resonated with bereaved people for decades since, was this: grief did not feel like sadness. It felt like fear.

“No one ever told me that grief felt so like fear. I am not afraid, but the sensation is like being afraid. The same fluttering in the stomach, the same restlessness, the yawning. I keep on swallowing.”

He described an inability to concentrate, a sense of unreality, the feeling of a door slamming shut. He described how the world continued indifferently around him — people shopping, talking, making plans — while he moved through it as though behind glass.

He was not writing for publication. He was writing to survive. The notebooks were a private act of making sense of something that refused to make sense.

What this means for bereaved parents today

Bereaved parents who describe their experience in the days and weeks after a pregnancy or infant loss often reach for similar language. Not sadness — that word is too quiet, too contained. Something more physical. A hollowness. A constant low-level alarm. The sense that the ground is not quite solid.

What Lewis described in 1960 fits what researchers have since found. Research on grief suggests that it switches on the body’s stress response, the same system that reacts to danger. The body responds to the absence of someone it was ready to protect and love almost as if to a threat that cannot be located or addressed.

This is why bereaved parents so often describe feeling unable to eat, unable to sleep properly, unable to concentrate. These are not signs of weakness or of grief going wrong. They are the body responding to something real and enormous, in the only way it knows.

Grief is not linear — and Lewis knew it

One of the most honest things about A Grief Observed is that it does not resolve neatly. Lewis goes through periods of relative calm only to be ambushed again. He observes himself with something close to detachment — noting the contradictions, the regressions, the unexpected moments when grief returns with full force from a direction he did not see coming.

This is the experience that bereaved parents describe at due dates, at anniversaries, at the sight of something ordinary — a certain quality of afternoon light, a song on the radio, someone else's baby in a supermarket. Grief does not follow a path. It circles.

What Lewis gave those who came after him was not a solution. It was permission — to feel what they actually felt, to describe it accurately, and to trust that the chaos of grief was not a sign that they were grieving wrongly.

About this piece

This article draws on the published text of A Grief Observed by C.S. Lewis (Faber & Faber, 1961) and on publicly available biographical accounts of his life and marriage. All quotes are from Lewis's own published writing. The neuroscience references reflect peer-reviewed research on grief and the stress response system, available in the MIMATIS research library at mimatis.org/research.

Healing Through Art

Memory boxes — what to put
in them, and why they help

A memory box is not about preserving grief. It is about acknowledging that your baby existed and that their existence mattered.

MEMORY  ·  REMEMBRANCE  ·  CONNECTION

When a baby dies, there is very little that can be held. The pregnancy was real. The baby was real. But in the days after a loss, there is so often an absence of tangible things — a room that was being prepared but was never used, a name that was chosen but rarely spoken aloud.

A memory box changes that. It gives grief something to hold.

What a memory box actually is

A memory box is a container — usually a small wooden or cardboard box — in which parents keep objects connected to their baby. It might be given to them by a hospital bereavement team. It might be something they put together themselves. The contents vary entirely, because the point is not the objects themselves but what they represent: acknowledgement that this baby was here, that they mattered, and that their parents remember them.

Many hospitals now offer memory boxes as part of bereavement care. In the UK, Sands provides memory boxes to many maternity units, and in the United States Now I Lay Me Down to Sleep (NILMDTS) offers free remembrance photography. But a memory box does not need to come from anywhere official. It can be assembled quietly, over time, by parents who are finding their way through.

A memory box is not about preserving grief. It is about acknowledging that your baby existed — and that their existence mattered.

What parents put inside them

There are no rules. These are some of the things parents most commonly include — not as a checklist, but as a gentle guide for those who are not sure where to begin.

01PhotographsMany parents treasure photographs taken in the hospital, including professional bereavement photography if it was available. These are often the only images that will ever exist of their baby.
02Handprints or footprintsMost hospital bereavement teams can help take ink or clay prints. These become profoundly precious over time — evidence of how small, how real, how present.
03A lock of hairIf the baby had hair, many parents ask for a small lock to be taken and kept. This is a request most bereavement teams are very familiar with and will help with gently.
04Hospital tags and recordsThe name tag, the hospital wristband, the record of weight and length. These small official records are among the few documents that confirm, in formal terms, that the baby existed.
05A blanket or garmentSomething the baby wore or was wrapped in. The smell fades eventually, but the object remains — something that touched them, that held them.
06Letters or cardsLetters written to the baby, cards from family and friends, anything that records the love that surrounded them — before and after their birth.

Why memory boxes help — what the research shows

Studies of parents after stillbirth find that many value the time they spent with their baby and the keepsakes they took home, and that few regret seeing and holding their baby. The evidence is not the same for every family, which is why these choices should always be offered and never pressed.

The evidence suggests that the act of acknowledgement — the hospital offering a memory box, a midwife asking if the parent would like photographs, a family member sitting with them as they carefully place objects inside — communicates something that words cannot always reach: your baby was real, your loss is real, and you are not grieving alone.

When you cannot make one straight away

Not every parent is ready to think about a memory box in the first days. Some find that the hospital provided one before they were able to receive it properly. Some find that they created one instinctively without knowing that was what it was called.

There is no correct time. A memory box can be started the day after a loss or a year later. Objects can be added over time — a pressed flower from the garden on an anniversary, a letter written on what would have been a birthday. A memory box is not a finished object. It is a living one.

Sources and further reading

Research on contact with the baby and keepsakes after stillbirth is explained on our Research page. Information on professional bereavement photography is available through NILMDTS (nowilaymedowntosleep.org) and Tommy's (tommys.org). Memory boxes and bereavement support are listed by country in the MIMATIS Find Help directory at mimatis.org.

Nature & Grief

Why grieving people
seek water

Rivers, oceans, lakes. Research on the nervous system is beginning to explain why so many bereaved parents are drawn to water in the weeks after loss.

NATURE  ·  THE NERVOUS SYSTEM  ·  GRIEF

There is something many bereaved parents notice in the days and weeks after a loss. An unexpected pull toward water. A river they walk to without planning to. A beach they find themselves at in the middle of winter. The bath, running long after it has gone cold.

This is not a coincidence, and it is not sentimental. There is an emerging body of research on what happens to the human nervous system when it encounters natural water — and it helps explain something that grieving people have known instinctively for a very long time.

What research on blue space tells us

The term “blue space” refers to natural water environments — rivers, lakes, coastlines, ponds, streams. Research on how these environments affect human psychology and physiology has grown significantly over the past decade, building on work in environmental psychology and neuroscience.

Studies link time near natural water with better mood and lower stress. Researchers at the University of Exeter found, for example, that people in England who live closer to the coast report better health and wellbeing, even after taking income and other factors into account.

The brain in grief is working hard — scanning, processing, adapting. Blue space appears to offer something the grieving mind rarely gets: permission to be still.

The reasons are not fully understood, but several explanations have been proposed. The steady sound of moving water and the view of an open horizon may help the body move out of alert and into rest, the work of the parasympathetic nervous system. The absence of visual complexity that characterises most natural water environments may reduce the cognitive load on a brain that is already working very hard.

Grief and the threat response

The body in acute grief is on high alert. Grief switches on the stress response, the same system that reacts to danger. This is why bereaved parents describe the physical symptoms of grief — the racing heart, the inability to eat, the constant low-level anxiety — that so closely resemble fear.

The parasympathetic nervous system, which time near water may help to engage, works against this state. It is not a cure for grief. But it is a relief from the constant physical burden of it. This may explain why so many bereaved parents describe feeling, for the first time in weeks, able to breathe properly when they are near water.

The Japanese practice of forest bathing

Related to the research on blue space is the Japanese practice of shinrin-yoku — forest bathing — which involves spending time slowly and attentively in a forest environment. Studies on shinrin-yoku published in peer-reviewed journals including Environmental Health and Preventive Medicine have shown measurable reductions in cortisol, blood pressure, and activity in the prefrontal cortex — the area of the brain most active during rumination and worry.

Shinrin-yoku is not about exercise or achieving anything. It is about presence — moving slowly, engaging the senses, allowing the environment to do what environments do when we are not too busy to notice them. For bereaved parents who feel unable to rest but also unable to act, this quality of gentle, purposeful presence can be easier to access than formal meditation or therapy.

What this means in practice

None of this is to suggest that a walk by a river will resolve grief. Grief cannot be resolved — it can only be carried more gently over time. But the research does suggest that the instinct many bereaved people have toward water and nature is a sound one, and that following it is not avoidance or escapism but a genuine act of physiological care.

If you find yourself drawn to water in the weeks and months after a loss — a particular stretch of canal, a specific beach, the sound of rain — trust that instinct. Your nervous system may know something your mind is still working out.

Sources

Research on blue space referenced in this article includes work from the University of Exeter's European Centre for Environment and Human Health. Research on shinrin-yoku is available in peer-reviewed journals including Environmental Health and Preventive Medicine. Research on grief and the stress response system is available in the MIMATIS research library at mimatis.org.

History & Stories of Meaning

Charles Darwin lost his
daughter Annie at ten years old

How one of history's greatest minds processed the most personal of losses — and what his private letters reveal about grief, love, and the limits of reason.

SPECIMEN DARWIN 1851 CHARLES DARWIN  ·  ANNE ELIZABETH DARWIN  ·  1851

Charles Darwin was fifty-nine when he published On the Origin of Species. He was forty-two when his daughter Annie died. The two events were a decade apart, but those who have studied Darwin's life closely have observed that they were not unconnected.

Anne Elizabeth Darwin died in April 1851 at the age of ten, after a prolonged illness. She was, by all accounts, Darwin's favourite child — bright, affectionate, deeply loved. Her death devastated him in a way that he never fully recovered from, and that he rarely spoke about in public for the rest of his life.

What the private letters reveal

What Darwin could not say publicly, he wrote privately. In letters to friends and family in the weeks after Annie's death, he described his grief with a directness that was unusual for a Victorian man of his position and reserve. He wrote of Annie's qualities in detail — her joyfulness, her curiosity, her tenderness — as though by describing her precisely he could hold on to something that was slipping away.

He also wrote what biographers have described as a “memorial essay” — a private document, never published in his lifetime, in which he recorded his memories of Annie in careful, loving detail. It reads not like a scientific document but like what it was: a bereaved father writing in the only way he knew how, trying to make something permanent out of something that had been taken.

He wrote of Annie's qualities in detail — her joyfulness, her curiosity, her tenderness — as though by describing her precisely he could hold on to something that was slipping away.

Grief at the edge of belief

Darwin had been moving away from religious belief for years before Annie's death. Her death completed that movement. He could not reconcile the death of a beloved, innocent child with a benevolent creator. The loss did not make him angry at God — it made God, for him, simply unthinkable. This is a response that many bereaved parents recognise.

What replaced religious comfort, for Darwin, was something more personal and harder to name. An intensification of his commitment to his work. A deepened tenderness toward his remaining children. A profound attention to the natural world that was both his vocation and, it seems, his solace.

What his grief made possible

This is not an inspirational story in the easy sense. Darwin did not “overcome” his grief or “turn it into something positive.” He carried it for the rest of his life. His wife Emma — who coped through her own religious faith — and Darwin grieved differently and sometimes at a distance, as bereaved couples so often do.

But his grief deepened him. The man who published On the Origin of Species in 1859 had been living with the knowledge of how much could be lost, how quickly, and how little reason there was for it. That knowledge is present, some historians argue, in the way he wrote about nature — with an unflinching attention to suffering and death as intrinsic to life, not as aberrations or punishments.

Annie is buried in Malvern, Worcestershire. Darwin rarely returned to visit her grave. But her name appears in his correspondence until the end of his life.

Sources and further reading

The primary sources for this article are Darwin's published correspondence (available through the Darwin Correspondence Project, darwinproject.ac.uk), his private memorial essay for Annie (held in the Darwin Archive at Cambridge University Library and published in Annie's Box by Randal Keynes, 2001), and the biographical accounts of Darwin's life by Janet Browne (Charles Darwin: Voyaging and Charles Darwin: The Power of Place). All biographical claims are drawn from these published, academically reviewed sources.

New Research

When grief lives in the body —
what the science says

Up to 60% of bereaved parents show symptoms of depression, anxiety or post-traumatic stress. Research helps explain why grief is felt in the body — and what that means for recovery.

Grief is not only emotional. It lives in the body. Bereaved parents consistently describe physical symptoms in the weeks and months after loss — disrupted sleep, changes in appetite, persistent low-level anxiety, an inability to concentrate, a heaviness that does not lift. These are not signs that something has gone wrong. They are the body responding to something real and enormous.

Up to 60 percent of bereaved parents show symptoms of depression, anxiety or post-traumatic stress after a pregnancy or infant loss. A peer-reviewed scoping review in the journal Trauma Care (2022) reports this figure.

Why grief feels like fear

The neuroscience helps explain what bereaved parents often struggle to describe. Research on grief suggests that it switches on the body’s stress response, the same system that reacts to danger. The body responds to the absence of someone it was ready to protect and love almost as if to a threat that cannot be located or addressed.

This is why the physical symptoms of grief so closely resemble fear. The racing heart, the inability to eat, the constant vigilance — these are not psychological weakness. They are a neurological response to genuine loss.

“Up to 60% of bereaved parents show symptoms of depression, anxiety or post-traumatic stress after a pregnancy or infant loss.”

What this means for bereaved parents

Understanding that grief is physical as well as emotional can be genuinely relieving. The exhaustion is real. The inability to concentrate is real. The way certain sounds or smells or qualities of light can trigger a wave of grief months after a loss — this is the nervous system doing what nervous systems do when they have experienced something traumatic.

It also means that physical care — sleep, food, time in nature, gentle movement — is not a distraction from grief. It is part of tending to it. And it means that if the symptoms of acute grief persist for months without improvement, that is a signal to seek professional support, not a sign of personal failure.

Sources

The figure comes from Berry SN, “The Trauma of Perinatal Loss: A Scoping Review”, Trauma Care 2022;2(3):392–407, doi.org/10.3390/traumacare2030032. More research on grief is explained on our Research page. Neurological information draws on published academic literature on grief and the stress response system.

Across Borders, Across Grief

Día de los Muertos —
beyond what you think you know

Mexico’s most recognised tradition of remembrance is far older, richer, and more tender than its popular image suggests.

Every year on the first and second of November, cemeteries across Mexico fill with light. Families carry marigolds whose colour and scent are said to guide the dead back to the living. They build ofrendas — elaborate altars with photographs, favourite foods, personal objects, water for the journey. They sit through the night with their dead.

Día de los Muertos is perhaps the most recognised grief tradition in the world, and also one of the most misunderstood. Its popular image has spread globally in ways that strip it of its depth. The tradition is not a celebration of death. It is a continuation of relationship. The dead are not being mourned as absent. They are being welcomed back, however briefly, as present.

What the ofrenda actually means

The altar is built to receive someone specific. It holds the particular details of a particular person — their photograph, the food they loved, the things that made them themselves. It is an act of radical specificity against the abstraction of loss.

For bereaved parents, this specificity is deeply resonant. The loss of a baby is often minimised by the wider world. The ofrenda tradition offers a different understanding: that even a short life has a specific presence worth honouring, worth returning to, worth keeping visible.

“The tradition is not a celebration of death. It is a continuation of relationship. The dead are being welcomed back as present.”

Día de los Muertos has pre-Columbian roots in Aztec and other Mesoamerican cultures. When Spanish colonisers arrived in the 16th century, they merged indigenous practices with Catholic All Saints’ Day and All Souls’ Day. The result is a tradition that is syncretic, layered, and deeply local.

What persists across these variations is the insistence that remembrance is active, not passive. You do not only grieve in private. You make something. You bring objects. You speak names aloud. You stay through the night.

Sources

Information draws on UNESCO’s Intangible Cultural Heritage documentation (Día de los Muertos was inscribed in 2008) and published ethnographic and historical sources on Mexican mourning traditions.

Partnerships

Better care when a baby dies. Together.

Every family who loses a baby, through miscarriage, stillbirth, neonatal death or sudden infant death, deserves good care and clear information. MIMATIS brings it together in one place, for every country. We cannot do it alone.

Write to us: contact@mimatis.org

Our goal

Global help, all in one place

One place

Information, support and remembrance for parents after every kind of pregnancy and baby loss, in their own language.

Every country

Some countries already offer families very good care. Many still do not. We want every family to receive the care the best hospitals already give.

Prevention

Around 1.9 million babies are stillborn every year (UNICEF, 2023), and some stillbirths and sudden infant deaths can be prevented. We want to share what helps, with medical teams at our side.

How we can work together

Three ways to partner

01

Hospitals & medical teams

  • Information for parents in their own language, to share before they go home
  • Remembrance events and talks for staff and families
  • Help us share, accurately, what can prevent stillbirth and sudden infant death
02

Companies & organisations

  • Sponsor a country guide or a translation
  • Sponsor memory boxes for parents and siblings, and comfort for families in hospital
  • Support employees after pregnancy or baby loss
03

Researchers

  • Share evidence on preventing stillbirth and SIDS, in plain language
  • Help us compare care between countries and show what works
  • Bring the voice of bereaved parents into better care
An open memory box holding a seed letter, a photo card, a name tag and pressed flowers
For businesses

Sponsor a memory box

Many parents leave hospital with empty arms and very few things to remember their baby by. A memory box gives them a safe place for what they do have: a photo, hand and foot prints, a lock of hair, the hospital bracelet, a name card.

Your company can sponsor memory boxes for parents, and for brothers and sisters, given to families through the hospitals we work with.

For parents

A keepsake box for photos, prints, a lock of hair and the hospital bracelet, with a MIMATIS seed letter they can plant in their baby’s memory.

For brothers and sisters

A smaller box for siblings, with something gentle to hold and a simple way to remember together, such as a seed letter to plant.

  1. 1You choose how many boxes, and for which country or hospital.
  2. 2We prepare them with the hospital’s bereavement team, so they fit what families need.
  3. 3With your permission, we thank you on this page. The boxes themselves carry no advertising.
Sponsor memory boxesWrite to contact@mimatis.org
How it starts

A simple first step

  1. 1

    Write to us

    A few lines about your hospital or organisation.

  2. 2

    We listen

    A short call about your goals and what already exists.

  3. 3

    We start small

    One clear first project, then we grow together.

Start a conversation

Write to Victoria, founder of MIMATIS

contact@mimatis.org

Asociación MIMATIS · non-profit association, registered no. 633.864 (Registro Nacional de Asociaciones, Spain)

Legal · GDPR

Privacy Policy

Last updated: 19 October 2026

1. Who is responsible for your data

Asociación MIMATIS, a non-profit association registered in the Registro Nacional de Asociaciones (Spain) under no. 633.864. Based in Puigcerdà, Spain. Contact: contact@mimatis.org.

2. What data we collect

We collect personal data only when you choose to give it to us:

DataPurposeLegal basis
Memorial Garden: your baby’s first name, the flower you choose and, if you wish, a yearTo show a flower in the Memorial GardenConsent (you choose to plant a flower)
Friends of MIMATIS: your email addressTo write to you a few times a year about the work of MIMATIS and ways to support itConsent (you tick the box and choose to join)
Emails you send us, including stories shared from the Memorial Garden page: your email address and what you writeTo reply to you. We publish a story only with your written permissionConsent and our legitimate interest in answering messages

We do not sell or share your data with anyone for their own purposes. We do not ask for your name when you plant a flower, so a flower cannot be linked to you.

3. Visiting the website and cookies

The website is hosted by Cloudflare. To deliver pages and protect the site against attacks, Cloudflare processes technical information such as your IP address and browser type. MIMATIS does not use this information to identify you.

MIMATIS uses no advertising or analytics cookies unless you agree to them. If a cookie notice appears and you choose Accept, we use Google tags (Google Ads and Google Analytics) to count visits and actions such as Friends of MIMATIS sign-ups, so we can see whether our free Google Ad Grants advertising reaches parents who need help. If you choose Decline, or do not answer, these tools are not loaded and no such cookies are set. You can change your choice at any time with “Cookie settings” at the bottom of the page.

Your browser keeps a small record of your cookie choice (in local storage) so we do not ask again on every visit.

4. Where your data is stored and for how long

Memorial Garden and Friends of MIMATIS — stored with Supabase, a database provider with servers in the European Union (Frankfurt, Germany). Flowers are kept permanently, as they form a lasting memorial, unless you ask us to remove one. Friends’ email addresses are kept until you ask to leave.

Emails — kept only as long as needed to reply and follow up.

Google tags — if you accept them, Google keeps measurement data according to its own retention settings, at most 14 months for Analytics data.

To leave Friends of MIMATIS or remove a flower, write to contact@mimatis.org.

5. Your rights

You have the right to:

Access — request a copy of the personal data we hold about you

Rectification — ask us to correct inaccurate data

Erasure — ask us to delete your data

Objection and restriction — object to or limit how we use your data

Withdraw consent — at any time, without affecting what was done before

Complaint — lodge a complaint with the Spanish data protection authority (AEPD) at aepd.es

To use any of these rights, write to contact@mimatis.org. We will respond within 30 days.

6. Services we use

FormSubmit — delivers stories sent from the Memorial Garden page to our inbox. It passes the message on and does not use it for anything else. formsubmit.co

Cloudflare — website hosting and security. cloudflare.com/privacypolicy

Supabase — database for the Memorial Garden and Friends of MIMATIS (EU servers). supabase.com/privacy

Google Fonts — loads the fonts used on the site; Google may record that a font was requested. policies.google.com/privacy

YouTube — some Journal entries show a preview image loaded from YouTube; videos open on YouTube itself.

Google Ads and Google Analytics — only if you accept them in the cookie notice (see section 3). How Google uses data

7. Changes to this policy

We will post any changes on this page with a new date.

Asociación MIMATIS · Statutes

Association Statutes

MIMATIS is a registered non-profit association in Spain (Registro Nacional de Asociaciones, Número 633864).

Article 1 — Name

The association is constituted under the name Asociación MIMATIS, hereinafter referred to as “the Association”.

Article 2 — Registered address

The registered address of the Association shall be established in Spain. The governing board may change the registered address within the same municipality by a simple majority vote, without requiring amendment to these statutes.

Article 3 — Territorial scope

The Association operates at national and international level. Activities are principally carried out through digital means and extend across Europe and globally. The Association shall be registered in the Registro Nacional de Asociaciones of Spain.

Article 4 — Duration

The Association is constituted for an indefinite period from the date of signing of the founding act.

Article 5 — Purpose and activities

The purpose of the Association is to provide free, accessible, and compassionate support, information, and community resources to parents who have experienced miscarriage, stillbirth, or neonatal loss, and to raise awareness of perinatal bereavement. To achieve this purpose, the Association shall carry out the following activities:

Operation and development of the MIMATIS digital platform (mimatis.community), providing verified support resources in multiple countries and languages

Curation and publication of peer-reviewed research on stillbirth, miscarriage, neonatal death, prevention, and grief

Collaboration with healthcare organisations, charities, researchers, and counsellors working in perinatal bereavement

Awareness-raising and advocacy activities regarding perinatal loss at European and international level

Fundraising and grant applications to support the Association’s non-profit activities

Article 6 — Non-profit nature

The Association is constituted without profit motive. Any income obtained through donations, grants, or activities shall be applied exclusively to the achievement of the Association’s purposes. No part of the income or assets of the Association shall be distributed to members.

Article 7 — Membership

Any natural or legal person who shares the purposes of the Association and accepts these statutes may apply for membership. The governing board shall decide on admission. Members shall have the right to vote at general assemblies, to stand for election to the governing board, to access all services and activities of the Association, and to receive information about its activities. Members shall have the obligation to pay any membership fee established by the general assembly, to comply with these statutes and the decisions of the governing bodies, and to collaborate in achieving the Association’s purposes.

Article 8 — Governing bodies

The Association shall be governed by a General Assembly of all members (the supreme governing body, meeting at least once per year) and a Governing Board (Junta Directiva), comprising at minimum a President, a Secretary, and a Treasurer. Board members shall be elected by the General Assembly for a period of four years and may be re-elected.

Article 9 — Economic resources

The Association’s resources shall consist of: membership fees (if established); donations and grants from public or private bodies; income from activities organised by the Association; and any other lawful income. The Association shall maintain accounting records in accordance with applicable Spanish law and shall prepare annual accounts to be presented to the General Assembly.

Article 10 — Dissolution

The Association may be dissolved by a decision of the General Assembly adopted by a two-thirds majority of members, or by judicial decision. In the event of dissolution, the remaining assets of the Association, after payment of any debts, shall be transferred to one or more non-profit organisations with similar purposes, as decided by the General Assembly.

Asociación MIMATIS is registered in the Registro Nacional de Asociaciones (Spain) under no. 633.864, registered on 12 August 2026.

A soft pink flower against a blue sky

Small things,
quietly growing.

Grow with us

MIMATIS began with one family and one wish: that no parent should have to search for help alone. Every country guide, every hospital project and every parent who finds support grows from people who care.

Become a Friend of MIMATIS. We will write a few times a year to share what your support makes possible, and you will be the first to know when you can help us do more.

A few emails a year. Asociación MIMATIS uses your email only to write to you as a Friend. It is stored in the EU and never shared or sold. To leave, reply to any of our emails or write to contact@mimatis.org. More in our .

Thank you. You are now a Friend of MIMATIS.

We will write a few times a year, nothing more.
Partners